

Small for gestational age fetus: clinical, anamnestic, and perinatal aspects
Sidelnikova M.D., Kan N.E., Tyutyunnik V.L., Soldatova E.E., Zolotareva A.P., Alieva L.E.
Objective. To identify the clinical characteristics and maternal history factors associated with adverse perinatal outcomes among pregnancies complicated by a small for gestational age fetus.
Materials and methods. This retrospective cohort study included 405 pregnant women with a prenatal diagnosis of a small for gestational age fetus who delivered at the V.I. Kulakov NMRC for OG&P between 2020 and 2025. This study included patients with singleton full-term pregnancies. Cases of multiple pregnancies, surrogacy, preterm birth, and pregnancies with diagnosed chromosomal abnormalities or fetal malformations were excluded from the study. The overall cohort was divided into two groups: those with favorable and those with unfavorable perinatal outcomes. An unfavorable outcome was defined as a neonatal condition with critical prognostic significance and a range of associated neonatal conditions (pathological adaptation). Clinical and anamnestic data, pregnancy and childbirth characteristics, and early neonatal period were assessed. Statistical analysis was performed using JASP (Student's t-test, Mann-Whitney U test, chi-square test, Fisher's exact test, p<0.05).
Results. The study found that 24% of pregnant women carrying a fetus diagnosed as small for gestational age experienced adverse perinatal outcomes, despite having no apparent signs of fetal distress during antenatal surveillance. The analysis revealed that differences in pregnancy outcomes were specifically associated with small for gestational age rather than the demographic or reproductive characteristics of the patients. Significant risk factors for adverse outcomes included low prenatal birth weight, history of spontaneous miscarriages and placenta-associated pregnancy complications, gynecological diseases (uterine fibroids and uterine anomalies), and pregnancy complications (threatened miscarriage, retrochorial hematoma, anemia, gestational hypertension, and oligohydramnios). Antenatal fetal weight assessment has limited prognostic value.
Conclusion. A small for gestational age fetus is a clinically heterogeneous condition with varying prognoses. Almost a quarter of small-for-gestational-age fetuses experience adverse perinatal outcomes, which represents a significant proportion and necessitates the search for new diagnostic options to identify these fetuses.
Authors' contributions. Sidelnikova M.D., Kan N.E., Tyutyunnik V.L., Soldatova E.E., Zolotareva A.P., Alieva L.E. – conception and design of the study, data acquisition, review of relevant literature, material processing and analysis, statistical analysis, drafting of the manuscript, editing of the manuscript.
Conflicts of interest. The authors have no conflicts of interest to declare.
Funding. There was no funding for this study.
Ethical Approval. The study was reviewed and approved by the Research Ethics Committee of the V.I. Kulakov NMRC for OG&P.
Generative Artificial Intelligence. No artificial intelligence tools were used in the preparation of this manuscript.
Patient Consent for Publication. All patients provided informed consent for the publication of their data.
Authors' Data Sharing Statement. The data supporting the findings of this study are available upon request from the corresponding author after approval from the principal investigator.
For citation: Sidelnikova M.D., Kan N.E., Tyutyunnik V.L., Soldatova E.E., Zolotareva A.P., Alieva L.E.
Small for gestational age fetus: clinical, anamnestic, and perinatal aspects.
Akusherstvo i Ginekologiya/Obstetrics and Gynecology. 2026; (9): 78-86 (in Russian)
https://dx.doi.org/10.18565/aig.2026.107
Keywords
small for gestational age fetus
fetal growth restriction
perinatal outcomes
clinical and anamnestic factors
Small for gestational age (SGA) fetuses are currently considered constitutionally small but healthy, with favorable perinatal outcomes. However, accumulating evidence indicates that this group is highly heterogeneous, encompassing a spectrum of conditions from healthy, constitutionally small fetuses to "pathologically" small fetuses with early manifestations of placental insufficiency and initial signs of fetal growth restriction (FGR) [1]. Several international guidelines consider fetuses with an estimated fetal weight below the 10th percentile to be at potential risk of adverse outcomes, reflecting the growing interest in the study of SGA fetuses.
Particular emphasis should be placed on the limitations of the current diagnostic approaches. Ultrasonographic measurements do not reliably determine whether a fetus is achieving its genetically determined growth potential and may yield false-positive results, particularly when a fetus is constitutionally small but demonstrates an appropriate growth trajectory. Therefore, identifying novel diagnostic markers that, when combined with clinical, medical history, and ultrasonographic data, could improve the diagnostic accuracy for SGA fetuses is highly relevant.
This study aimed to identify the clinical characteristics and maternal history factors associated with adverse perinatal outcomes in pregnancies complicated by SGA fetuses.
Materials and methods
Data from 405 pregnant women with an antenatal diagnosis of an SGA fetus who delivered at V.I. Kulakov National Medical Research Centre for Obstetrics, Gynecology and Perinatology between 2020 and 2025 were retrospectively analyzed. The study included patients with singleton pregnancies who delivered at >37 weeks' gestation. The exclusion criteria were multiple pregnancies, surrogate motherhood, preterm delivery, and diagnosed fetal chromosomal abnormalities or congenital malformations. Clinical and medical history data were collected, and the characteristics of pregnancy, delivery, and perinatal outcomes were described. Data were obtained from archived obstetric and neonatal medical records of the patients. The early neonatal period was assessed in the newborns. A predefined list of potential neonatal conditions was divided into two categories: composite adverse perinatal outcome (CAPO), comprising events of critical prognostic importance, and a spectrum of concomitant neonatal conditions analyzed as secondary indicators of neonatal clinical status. The neonatal outcomes considered and their clinical relevance are presented in Table 1.

Statistical analysis
Statistical analysis was performed using JASP version 0.9.1 (Netherlands). The choice of statistical tests depended on the type and distribution of data. Normally distributed continuous variables were analyzed using the Student's t-test, whereas the Mann–Whitney U test was used for non-normally distributed variables. Categorical variables were compared using the chi-square or Fisher's exact test. Statistical significance was set at p<0.05.
Results
The initial analysis of the overall patient cohort involved stratification into three groups according to perinatal outcome: favorable outcome, CAPO, and concomitant neonatal conditions. For statistical analysis, the groups with critical conditions and neonatal morbidity were combined into a single category of newborns with pathological adaptation (adverse outcomes). This consolidation is clinically justified, as both types of conditions represent a deviation from normal neonatal adaptation and require increased medical care. An additional analysis of the structure of these two condition types within the consolidated group was conducted. Thus, based on predefined criteria, an adverse outcome group (study group, n=97), representing 24% of the total patient population, and a favorable outcome group (control group, n=308) were identified. This stratification allowed for the subsequent evaluation of the impact of various clinical factors on the probability of adverse outcomes. The characteristics of the study groups are presented in Table 2.


A comparison of the clinical and anamnestic characteristics of pregnant women demonstrated that the groups were comparable across most parameters, including age, height, body mass index (BMI), parity, use of assisted reproductive technology (ART) for conception, and paternal age. The only statistically significant risk factor identified during the analysis was pre-pregnancy underweight status. Pre-pregnancy underweight was observed in 15/97 (15.6%) patients in the study group compared with 34/308 (11%) in the control group (p<0.05). Analysis of obstetric history revealed that the study group had a significantly higher rate of previous spontaneous miscarriages than the control group; furthermore, the study group exhibited a higher incidence of "great obstetric syndromes" (preeclampsia, preterm birth, and FGR) during prior pregnancies.
Analysis of the frequency and structure of extragenital diseases revealed no statistically significant differences between the groups. Evaluation of the pattern of gynecological disorders identified several statistically significant differences between the groups. In the study group, large uterine leiomyomas, congenital uterine anomalies (saddle-shaped, unicornuate, bicornuate, and uterine didelphys), intrauterine adhesions, and a history of uterine curettage were diagnosed significantly more frequently.
The features of the pregnancy course were analyzed by trimester. In the first trimester, patients in the study group had a significantly higher incidence of threatened miscarriage and retrochorionic hematoma formation. Furthermore, according to first-trimester combined prenatal screening data, they were at a higher risk of developing preeclampsia. A high risk of FGR was also more prevalent in the study group, although the difference did not reach statistical significance. Evaluation of key test results conducted in the second trimester of pregnancy revealed no statistically significant differences between the groups. Analysis of the third trimester revealed statistically significant differences between the groups regarding the incidence of anemia, gestational hypertension, and oligohydramnios, all of which occurred significantly more frequently in the study group than in the control group. Cervical insufficiency occurred slightly more frequently in the study group (4/97 [4.8%] vs. 7/308 [2.1%]), but the difference was not statistically significant (p=0.177).
When examining the characteristics of labor and delivery in both groups, the gestational age at delivery and rate of spontaneous vaginal delivery were comparable. The rate of labor induction was similar in both groups. Although the overall operative delivery rate did not differ statistically between the groups, emergency operative delivery (both abdominal and vaginal) was required significantly more frequently in the study group. However, analysis of the indications for emergency delivery demonstrated that fetal distress, despite occurring with a slightly higher frequency in the study group (14/97 [16.5%] vs. 33/308 [10%]), did not reach statistical significance (p=0.084). Notably, premature detachment of a normally implanted placenta (placental abruption), an indication for emergency operative delivery with a profound impact on fetal condition, occurred significantly more frequently in the study group (5/97 [5.2%] vs. 2/308 [0.65%], p=0.004). No differences were identified between the groups regarding the total duration of labor, length of the first and second stages, or rupture-to-delivery interval.
A discrepancy was observed between antenatal fetal weight estimation and actual birth weights. Although the study included only fetuses categorized as SGA antenatally, only 48% (194/405) were classified as low birth weight newborns after delivery; a substantial proportion (42%, 170/405) had normal birth weight, and 10% (41/405) were categorized as small for gestational age newborns. The distribution of neonatal anthropometric parameters was examined in both groups of patients. In the favorable outcome group, most newborns had normal weight (47%, 145/308), although a significant proportion (45%, 137/308) was classified as having low birth weight. In the adverse outcome group, there was a decrease in the proportion of normal-weight newborns (29%, 28/97) and an increase in the proportion of SGA (56%, 54/97) and low-weight newborns (15%, 15/97). Group comparison showed statistically significant differences: the favorable outcome group had a significantly higher number of normal-weight newborns and a significantly lower number of low-weight newborns than the adverse outcome group (p<0.05) (Fig. 1).
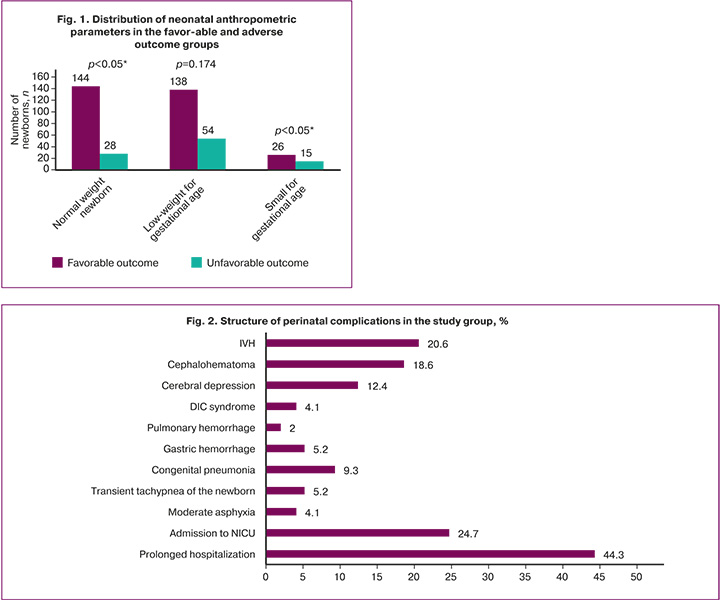
The structure of the perinatal complications are shown in Figure 2. The analysis revealed that the most significant categories were neonatal morbidity and suboptimal birth parameters (birth asphyxia and the need for admission to the neonatal intensive care unit [NICU]). Within the structure of neonatal morbidity, central nervous system (CNS) disorders made the largest contribution (33%), dominated by intraventricular hemorrhage (IVH) (20/97 [20.6%]), CNS depression (12/97 [12.4%]), cephalohaematomas (18/97 [18.6%]), and infectious/inflammatory diseases (9/97 [9%]). Hematologic disorders (4/97 [4.1%]), gastrointestinal disorders (5/97 [5.1%]), and respiratory system disorders (7/97 [7.2%]) occurred less frequently.
Discussion
The findings indicate that adverse perinatal outcomes occurred in nearly one-quarter (24%) of pregnancies complicated by a SGA fetus, despite the absence of overt signs of severe fetal compromise during antenatal surveillance. Stratification into two groups based on neonatal outcomes enabled the identification of several factors associated with an increased risk of adverse perinatal outcomes.
The results demonstrated that the study groups were comparable with respect to most clinical and medical history characteristics. This suggests that the observed differences in pregnancy outcomes were likely directly associated with antenatal fetal smallness rather than with the patients' general demographic or reproductive characteristics. Nevertheless, the statistically significant difference in the prevalence of pre-pregnancy underweight between the two groups may indicate its potential role in the development of the condition under study. Underweight is a recognized risk factor for adverse pregnancy outcomes, including low birth weight [2, 3].
Analysis of obstetric history revealed a significantly higher frequency of previous spontaneous miscarriages in the study group. This finding may indicate the presence of unidentified factors predisposing these patients to pregnancy loss, such as genetic abnormalities, immunological factors, or coagulation disorders, as supported by the current literature [4]. The observed trend toward a higher frequency of "major obstetric syndromes" (preeclampsia, preterm birth, and FGR) in previous pregnancies in the study group may indicate an increased risk of recurrence of these complications in the current pregnancy, underscoring the need for close surveillance and preventive measures in patients with an adverse obstetric history [5]. In addition, a study by Barzilai R. et al. involving a cohort of 926 women with a history of delivering a small-for-gestational-age infant supports the possibility of a genetic component in the transmission of this trait [6].
No statistically significant differences were observed in the overall frequency or distribution of extragenital diseases. The prevalence of the most common conditions, including diseases of the visual, respiratory, cardiovascular, and gastrointestinal systems, was comparable between the two groups.
The findings revealed substantial differences in the distribution of gynecological conditions between the study groups. Large uterine fibroids, uterine structural anomalies, intrauterine adhesions, and a history of uterine curettage were significantly more common in the study group. These gynecological conditions may impair implantation and placental development, potentially explaining the higher frequency of suboptimal fetal growth in these patients [7, 8].
Analysis of the course of pregnancy identified several features in the study group, indicating an increased risk of adverse outcomes. During the first trimester, threatened miscarriage and retrochorionic hematoma were significantly more common in the study group. Even small retrochorionic hematomas may adversely affect placental function, particularly in early pregnancy, when the active development of the vascular network occurs [9]. Threatened miscarriage is often associated with hormonal disturbances, inflammatory processes, and hemostatic abnormalities, which may adversely affect placental development and fetal growth. Inflammation associated with threatened miscarriage may lead to endothelial dysfunction and thrombus formation in placental vessels, thereby exacerbating fetal hypoxia. In addition, a high risk of preeclampsia according to first-trimester prenatal screening was significantly more common in the study group, whereas the risk of FGR, although somewhat higher, did not differ significantly between groups. During the second trimester, no statistically significant differences in the frequency of complications were observed between the groups, which may indicate that the effects of these conditions become apparent later in gestation. During the third trimester, anemia, gestational hypertension, and oligohydramnios were significantly more common in the study group. All of these conditions may contribute to fetoplacental insufficiency, which, in turn, may adversely affect fetal growth and development. Thus, our observations support the hypothesis that impaired placental development in early pregnancy may be a key pathogenic link underlying complications that manifest in the third trimester [10].
The results demonstrated that, despite comparable gestational ages at delivery and similar frequencies of vaginal delivery in the two groups, there was a trend toward a higher frequency of emergency operative deliveries in the study group. The frequency of induced labor was equivalent between the groups, allowing the influence of labor induction on the observed differences to be excluded from the study. Notably, although the frequency of fetal distress was somewhat higher in the study group, the difference was not statistically significant. This suggests that the increased frequency of emergency operative deliveries was likely attributable not primarily to an immediate deterioration in fetal condition but rather to other factors associated with the course of pregnancy in the study group.
The results demonstrate substantial discordance between antenatal fetal weight assessment and postnatal assessment of neonatal weight and length, according to the INTERGROWTH-21st criteria. The finding that only 48% of fetuses classified as SGA antenatally were subsequently confirmed to be low-weight newborns indicates the limited predictive value of ultrasound-estimated fetal weight and reflects differences in the methodologies used for assessment: antenatal estimates are based on fetal biometric parameters and mathematical formulas, whereas postnatal assessment according to INTERGROWTH-21st is based on percentile curves that account for gestational age, sex, and ethnicity [11].
A comparison of weight categories according to the INTERGROWTH-21st standards demonstrated a predominance of small neonates in the group with adverse outcomes, which likely indicates undiagnosed FGR in the antenatal stage. This finding underscores the need to improve the diagnostic approaches for the detection of FGR [12]. Analysis of the pattern of perinatal complications showed that adverse perinatal outcomes were largely attributable to CNS injury and impaired neonatal adaptation, consistent with the findings reported by other authors [13, 14].
The predominance of CNS injuries may be associated with hypoxic–ischemic injury secondary to undiagnosed fetoplacental insufficiency and immature regulatory mechanisms in low-weight newborns [3, 15]. Cephalohematomas may reflect not only mechanical birth trauma but also hemostatic abnormalities characteristic of low-weight neonates. The relatively low frequency of hematological, gastrointestinal, and respiratory disorders is consistent with findings from other studies, indicating the predominant role of cerebral complications in the pattern of morbidity among children in this population [12].
Conclusion
In conclusion, the clinical heterogeneity of the SGA fetal population was demonstrated, as reflected in the variability in prognosis, indicating the need for differentiated approaches to the management of such pregnancies. Nearly one-quarter of SGA fetuses experienced adverse perinatal outcomes, representing a substantial proportion and underscoring the importance of developing new diagnostic approaches.
References
- Miranda J., Paules C., Noell G., Youssef L., Paternina-Caicedo A., Crovetto F. et al. Similarity network fusion to identify phenotypes of small-for-gestational-age fetuses. iScience. 2023; 26(9): 107620. https://dx.doi.org/10.1016/j.isci.2023.107620
- Yang L., Feng L., Huang L., Li X., Qiu W., Yang K. et al. Maternal factors for intrauterine growth retardation: systematic review and meta-analysis of observational studies. Reprod. Sci. 2023; 30(6): 1737-45. https://dx.doi.org/10.1007/s43032-021-00756-3
- Devaguru A., Gada S., Potpalle D., Dinesh Eshwar M., Purwar D. The prevalence of low birth weight among newborn babies and its associated maternal risk factors: a hospital-based cross-sectional study. Cureus. 2023; 15(5): e38587. https://dx.doi.org/10.7759/cureus.38587
- Fetal Growth Restriction. ACOG Practice Bulletin, Number 227. Obstet. Gynecol. 2021; 137(2): e16-e28. https://dx.doi.org/10.1097/AOG.0000000000004251
- Dapkekar P., Bhalerao A., Kawathalkar A., Vijay N. Risk factors associated with intrauterine growth restriction: a case-control study. Cureus. 2023; 15(6): e40178. https://dx.doi.org/10.7759/cureus.40178
- Barzilai R., Bronshtein M., Steinberg M., Weiner Z., Gover A. Small for gestational age: the familial perspective. J. Matern. Fetal Neonatal. Med. 2022; 35(20): 3840-4. https://dx.doi.org/10.1080/14767058.2020.1841160
- Fasoulakis Z., Koutras A., Antsaklis P., Theodora M., Valsamaki A., Daskalakis G. et al. Intrauterine growth restriction due to gestational diabetes: from pathophysiology to diagnosis and management. Medicina (Kaunas). 2023; 59(6): 1139. https://dx.doi.org/10.3390/medicina59061139
- Mohammad N., Sohaila A., Rabbani U., Ahmed S., Ahmed S., Ali S.R.Maternal predictors of intrauterine growth retardation. J. Coll. Physicians Surg. Pak. 2018; 28(9): 681-5. https://dx.doi.org/10.29271/jcpsp.2018.09.681
- Liang W., Yan X., Shi Y., Chen B., An L., Huang B. et al. Association between graded subchorionic hematoma and adverse pregnancy outcomes in singleton pregnancies: a prospective observational cohort study. Arch. Gynecol. Obstet. 2024; 309(2): 541-9. https://dx.doi.org/10.1007/s00404-023-06943-8
- Щеголев А.И., Туманова У.Н., Серов В.Н. Роль плаценты в развитии поражений головного мозга новорожденного. Акушерство и гинекология. 2023; 8: 38-47. https://dx.doi.org/10.18565/aig.2023.185 [Shchegolev A.I., Tumanova U.N., Serov V.N. The role of the placenta in the development of brain damage in newborns. Obstetrics and Gynecology. 2023; (8): 38-47. (in Russian). https://dx.doi.org/10.18565/aig.2023.185].
- Волочаева М.В., Тимофеева А.В., Федоров И.С., Кан Н.Е., Тютюнник В.Л., Рыжова К.О., Гасымова Ш.Р. Модель диагностики задержки роста плода с использованием функциональных методов исследования. Акушерство и гинекология. 2025; 2: 31-9. https://dx.doi.org/10.18565/aig.2025.15 [Volochaeva M.V., Timofeeva A.V., Fedorov I.S., Kan N.E., Tyutyunnik V.L., Ryzhova K.O., Gasymova Sh.R. Model for diagnosing fetal growth restriction using functional research methods. Obstetrics and Gynecology. 2025; (2): 31-9. (in Russian). https://dx.doi.org/10.18565/aig.2025.15].
- Волочаева М.В., Кан Н.Е., Тютюнник В.Л., Леонова А.А., Солдатова Е.Е., Рыжова К.О. Особенности постнатального развития детей с задержкой роста (катамнестическое исследование). Акушерство и гинекология. 2025; 3: 65-71. https://dx.doi.org/10.18565/aig.2025.32 [Volochaeva M.V., Kan N.E., Tyutyunnik V.L., Leonova A.A., Soldatova E.E., Ryzhova K.O. Features of postnatal development of children with growth retardation (follow-up study). Obstetrics and Gynecology. 2025; (3): 65-71. (in Russian). https://dx.doi.org/10.18565/aig.2025.32].
- Meler E., Mazarico E., Eixarch E., Gonzalez A., Peguero A., Martinez J. et al. Ten-year experience of protocol-based management of small-for-gestational-age fetuses: perinatal outcome in late-pregnancy cases diagnosed after 32 weeks. Ultrasound Obstet. Gynecol. 2021; 57(1): 62-9. https://dx.doi.org/10.1002/uog.23537
- Alda M.G., Holberton J., MacDonald T.M., Charlton J.K. Small for gestational age at preterm birth identifies adverse neonatal outcomes more reliably than antenatal suspicion of fetal growth restriction. J. Matern. Fetal Neonatal. Med. 2023; 36(2): 2279017. https://dx.doi.org/10.1080/14767058.2023.2279017
- Sun L., Lee F.T., Milligan N., Zhu M., van Amerom J.F.P., Saini B.S. et al. Neurodevelopment among infants with late-onset fetal growth restriction. JAMA Netw. Open. 2025; 8(6): e2517360. https://dx.doi.org/10.1001/jamanetworkopen.2025.17360
Received 01.04.2026
Accepted 01.09.2026
About the Authors
Maria D. Sidelnikova, Obstetrician-Gynecologist at the 1st Obstetric Physiological Department, Academician V.I. Kulakov National Medical Research Center for Obstetrics, Gynecology and Perinatology, Ministry of Health of Russia, 117997, Russia, Moscow, Ac. Oparina str., 4, +7(903)220-45-13, m_sidelnikova@oparina4.ru,https://orcid.org/0000-0002-0805-4703
Natalia E. Kan, Professor, Dr. Med. Sci., Honored Scientist of the Russian Federation, Deputy Director General for Research – Director of the Institute of Obstetrics, Academician V.I. Kulakov National Medical Research Center for Obstetrics, Gynecology and Perinatology, Ministry of Health of Russia, 117997, Russia, Moscow,
Ac. Oparina str., 4, kan-med@mail.ru, Researcher ID: B-2370-2015, SPIN-code: 5378-8437, Authors ID: 624900, Scopus Author ID: 57008835600,
https://orcid.org/0000-0001-5087-5946
Victor L. Tyutyunnik, Professor, Dr. Med. Sci., Honored Doctor of the Russian Federation, Leading Researcher at the Center of Scientific and Clinical Researches, Academician V.I. Kulakov National Medical Research Center for Obstetrics, Gynecology and Perinatology, Ministry of Health of Russia, 117997, Russia, Moscow, Ac. Oparina str., 4, tioutiounnik@mail.ru, Researcher ID: B-2364-2015, SPIN-code: 1963-1359, Authors ID: 213217, Scopus Author ID: 56190621500, https://orcid.org/0000-0002-5830-5099
Ekaterina E. Soldatova, PhD, Researcher at the Institute of Obstetrics, Academician V.I. Kulakov National Medical Research Center for Obstetrics, Gynecology and Perinatology, Ministry of Health of Russia, 117997, Russia, Moscow, Ac. Oparina str., 4, katerina.soldatova95@bk.ru, https://orcid.org/0000-0001-6463-3403
Anna P. Zolotareva, PhD candidate, Academician V.I. Kulakov National Medical Research Center for Obstetrics, Gynecology and Perinatology, Ministry of Health of Russia, 117997, Russia, Moscow, Ac. Oparina str., 4; Obstetrician-Gynecologist, Day Hospital Department for Pregnancy Examination, Primorsky Krai Perinatal Center, 690042, Russia, Vladivostok, Mozhayskaya str., 1B, serebriakovanna@gmail.com, https://orcid.org/0000-0001-7014-2627
Leyla E. Alieva, PhD Student, Academician V.I. Kulakov National Medical Research Center for Obstetrics, Gynecology and Perinatology, Ministry of Health of Russia,
117997, Russia, Moscow, Ac. Oparina str. 4, leylaalieva00@mail.ru, https://orcid.org/0009-0008-3417-6721
Corresponding author: Maria D. Sidelnikova, m_sidelnikova@oparina4.ru
Similar Articles

